Latest Blog

DME MACs Issue a Correct Coding Bulletin for Diabetic Shoe Inserts

On February 1, 2018 the four Durable Medical Equipment Medicare Administrative Contractors (DME MACs) issued a correct coding bulletin that addresses proper coding of diabetic shoe inserts described by HCPCS codes A5512, A5513, and the recently created K0903 which describes custom fabricated, total contact inserts that are manufactured through a direct milling process that utilizes a digital model of the patient’s foot to direct a CAM based system in the fabrication of the insert.

The correct coding bulletin indicates that the PDAC coding redetermination review project, which was initially announced in August of 2017 and scheduled to be completed by June 1, 2018 has been extended to a new completion date of August 1, 2018 to allow manufacturers and central fabricators additional time to submit applications for their respective products. All diabetic inserts billed to Medicare using A5513 or K0903 must be listed on the PDAC product classification list no later than August 1, 2018. Inserts that are not included on the PDAC list by August 1, 2018 must be coded as A9270 and will be considered non-covered by Medicare.

Direct milled inserts described by K0903 must be billed using K0903 for dates of service on or after April 1, 2018, the effective date of the code regardless of how they are currently listed on the PDAC product classification list. In addition, manufacturers and central fabricators of direct milled inserts must submit their product(s) to PDAC for review no later than April 1, 2018.

While K0903 is effective for date of service on or after April 1, 2018, the Centers for Medicare and Medicaid Services (CMS) has not yet issued the Medicare fee schedule amount for K0903. As AOPA previously reported, the FAQ document that accompanied the announcement of the proposed changes to the DMEPOS quality standards that included direct milled, custom fabricated diabetic inserts in the definition of “molded to patient model” included a proposed 14% reduction in the Medicare fee schedule for direct milled inserts. AOPA has challenged this proposal based on several bases, including provisions within CMS’ own instructions to contractors that require the direct crosswalk of established Medicare fee amounts when a single code is exploded into two or more similar codes, and final decision on the fee schedule amount is still pending within CMS leadership. AOPA believes that this instruction applies to the creation of K0903 as it is similar to existing code A5513. AOPA will continue to monitor CMS resources for information regarding the Medicare fee schedule for K0903 and will communicate any new information to AOPA members as soon as possible.

View the DME MAC correct coding bulletin.

Questions regarding this issue may be directed to Joe McTernan at jmcternan@aopanet.org or Devon Bernard at dbernard@aopanet.org.
CMS and VA Announce Partnership to Strengthen Prevention of Waste, Fraud, and Abuse Efforts

On January 23, 2018, the Centers for Medicare and Medicaid Services (CMS) and the US Department of Veterans Affairs (VA) announced a new partnership in which they will share data, data analytics and best practices in an effort to improve both agencies efforts to combat waste, fraud, and abuse in their respective healthcare delivery systems.

The VA and CMS represent the two largest public-private healthcare organizations in the country. According to the press release, the partnership will allow the VA to take advantage of gains in data analytics developed by CMS through its Center for Program Integrity.

While the press release discussed general efforts to improve efforts to eliminate waste, fraud, and abuse and made no specific mention of orthotics and prosthetics, the announcement is a clear indication that the VA will be placing increased scrutiny on all providers in the future. While AOPA supports efforts to eliminate fraud and abuse within the healthcare sector, it must be done in a manner that does not inadvertently lead to unnecessary restriction to access to medically necessary care for veterans and Medicare beneficiaries.

View the CMS/VA press release.

Questions regarding this issue may be directed to Joe McTernan at jmcternan@aopanet.org or Devon Bernard at dbernard@aopanet.org.
OIG Work Plan Targets OTS Spinal and OTS Knee Orthoses

As part of its update to its 2018 work plan, the Department of Health and Human Services Office of Inspector General (OIG) announced that, based on abnormally high utilization and unusually high improper payment rates, two off the shelf (OTS) HCPCS codes that describe lumbar sacral orthoses (L0648 and L0650) and one OTS knee orthosis code (L1833) will be added as an area of focus for investigation by the OIG. All three codes identified by the OIG are part of the split code set created by CMS in 2014 that differentiated OTS orthoses from those that require the expertise of a certified orthotist or an equivalently trained professional.

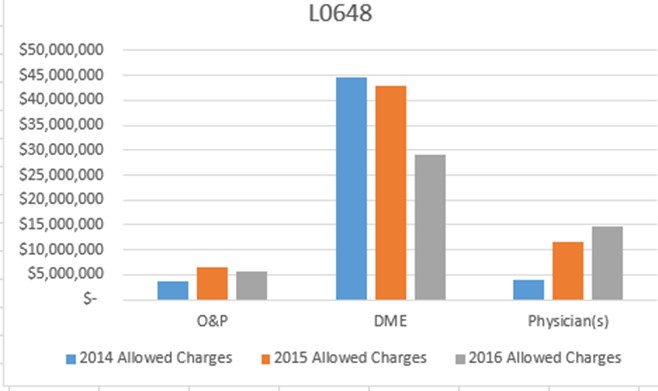
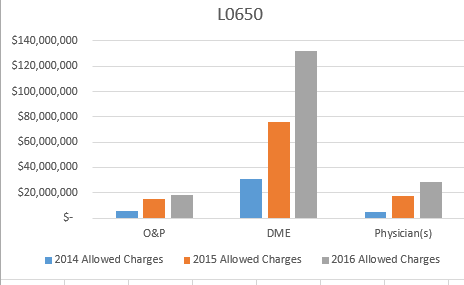
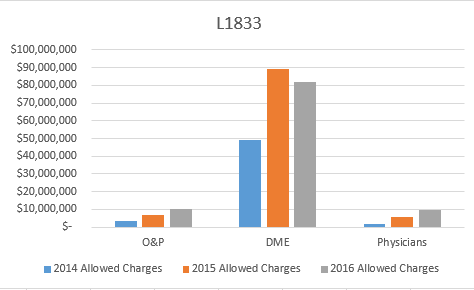
In its announcement the OIG reported that, since 2014, claims for the three OTS codes have grown by 97% with allowed charges rising to $349 million in 2016.  The OIG plans to explore questionable billing practices for these three codes including the lack of medical necessity documentation from referring providers and instances where no patient/physician encounter occurred within the 12 months prior to provision of the orthosis.

Based on Medicare utilization data from 2014 until 2016 AOPA has determined that less than 10% of the OTS devices described by L0648, L0650, and L1833 were provided by traditional O&P companies. The vast majority of these devices, over 65%, were provided by DME suppliers without certified O&P professionals on staff.  The graphs below show the overall utilization of each code by O&P providers, DME providers, and physicians.


While traditional O&P providers represent a small percentage of the overall utilization of these three codes, it remains wise to make sure that, when providing OTS orthoses described by these codes and any other codes, proper medical necessity documentation is maintained by the ordering physician and all Medicare policy requirements have been met.  While L0648, L0650, and L1833 have not previously been identified as approved for RAC review, the outcome of the OIG review may possibly lead to additional audit activity by the RAC and other contractors.

Questions regarding this issue may be directed to Joe McTernan at jmcternan@aopanet.org or Devon Bernard at dbernard@aopanet.org.

CMS Issues Temporary “K” Code to Describe Direct Milled, Custom Fabricated Diabetic Inserts

On January 11, 2018, as part of its quarterly HCPCS update, the Centers for Medicare and Medicaid Services (CMS) issued a new HCPCS code to describe direct milled, custom fabricated diabetic inserts.  The new code is effective April 1, 2018 reads as follows:

K0903–For Diabetics Only, Multiple Density Insert, Made By Direct Carving With CAM Technology From A Rectified CAD Model Created From A Digitized Scan Of The Patient, Total Contact With Patient’s Foot, Including Arch, Base Layer Minimum Of 3/16 Inch Material Of Shore A 35 Durometer (Or Higher), Includes Arch Filler And Other Shaping Material, Custom Fabricated, Each

The new code is categorized as a “K” code which is technically a temporary code designed to allow CMS to track utilization prior to deciding whether to issue a permanent HCPCS code, in this case an “A” code.  Any codes that are created mid-year must be issued as “K” codes.

The purpose of the K code is to differentiate between custom fabricated diabetic inserts that are molded over a physical model of the patient’s foot (A5513) from those that are direct milled based on a digital or virtual model of the patient’s foot.  While both manufacturing processes result in functionally identical custom fabricated, total contact inserts, CMS has indicated that direct milled inserts, while qualified to meet the DMEPOS Supplier Standards definition of molded to patient model, do not meet the requirements of A5513.  AOPA has challenged this premise and is continuing to discuss this issue with high ranking CMS officials.

A fee schedule for K0903 has not been released.  CMS has previously indicated that Medicare reimbursement for direct milled inserts would be 14% lower than the current reimbursement rate for custom molded inserts described by A5513 due to the lack of creation of a physical model of the patient’s foot.  AOPA disagrees with CMS on this issue and provided extensive comments regarding reimbursement for direct milled inserts in its formal submission to CMS.

AOPA will continue to follow this issue closely and will provide additional information upon its release by CMS.

Questions regarding this issue may be directed to Joe McTernan at jmcternan@aopanet.org or Devon Bernard at dbernard@aopanet.org.

CMS Finalizes Revised DMEPOS Quality Standards

On January 9, 2018, CMS published its final changes to the DMEPOS Quality Standards, specifically the standards that address the definition of the term “molded to patient model” as it relates to the provision of custom fabricated diabetic inserts.

CMS made only one small change to the definitions it included in its November 2, 2017 proposed rule that included direct milled, custom fabricated diabetic inserts made using a digital or virtual model of the patient’s foot in the proposed definition of the term “molded to patient model.” There was no change in the proposed language in the final changes to the DMEPOS Quality Standards. CMS did include the use of a foam box impression as an acceptable means of creating an impression of the patient’s foot for use in the creation of a positive model of the patient’s foot.

While AOPA is generally pleased with the changes to the DMEPOS Quality Standards, it remains concerned regarding CMS’ indication that direct milled, custom fabricated inserts will be reimbursed at a significantly lower rate (14% lower) than inserts made from a physical model of the patients foot that are currently described by HCPCS code A5513. In its response to AOPA’s and other’s comments regarding this issue, CMS stated that, “The first step CMS must take is to finalize the DMEPOS Quality Standards. Once that step is completed, CMS can assess what needs to be done in order to implement any changes to the quality standards.”

Obviously, the failure of CMS to address concerns over different reimbursement rates for direct milled diabetic inserts that are essentially identical in structure and function to inserts molded over a positive model of the patient’s foot can be seen as disappointing, but on the other hand, if CMS were locked in to the idea of the suggested 14% decrease for scanned devices, they could have easily closed the door, but they didn’t. AOPA believes we made some inroads with our arguments: (1) that FDA, not CMS has authority as to manufacturing processes; (2) that very significant harm could arise for compromised diabetic patients if there are any new impediment to receiving proper shoes/inserts; and (3) that provisions in CMS’ own Claims Processing Manual do not afford CMS the authority to reduce (or increase) prices when exploding a code into two similar codes; so in that respect, we are cautiously optimistic. AOPA will continue to address this issue with high ranking CMS officials to ensure that patients continue to have access to the highest quality, most clinically appropriate care.

The final revisions to the DMEPOS Quality Standards as well as a summary of comments received by CMS, and their responses may be viewed on the CMS website.

Read the comments AOPA submitted to CMS on diabetic shoes inserts and quality standards.

Questions regarding this issue may be directed to Joe McTernan at jmcternan@aopanet.org or Devon Bernard at dbernard@aopanet.org.